
The $7.7 Billion Question: Why Hospitals Can't Afford to Ignore Internal Float Pools Anymore
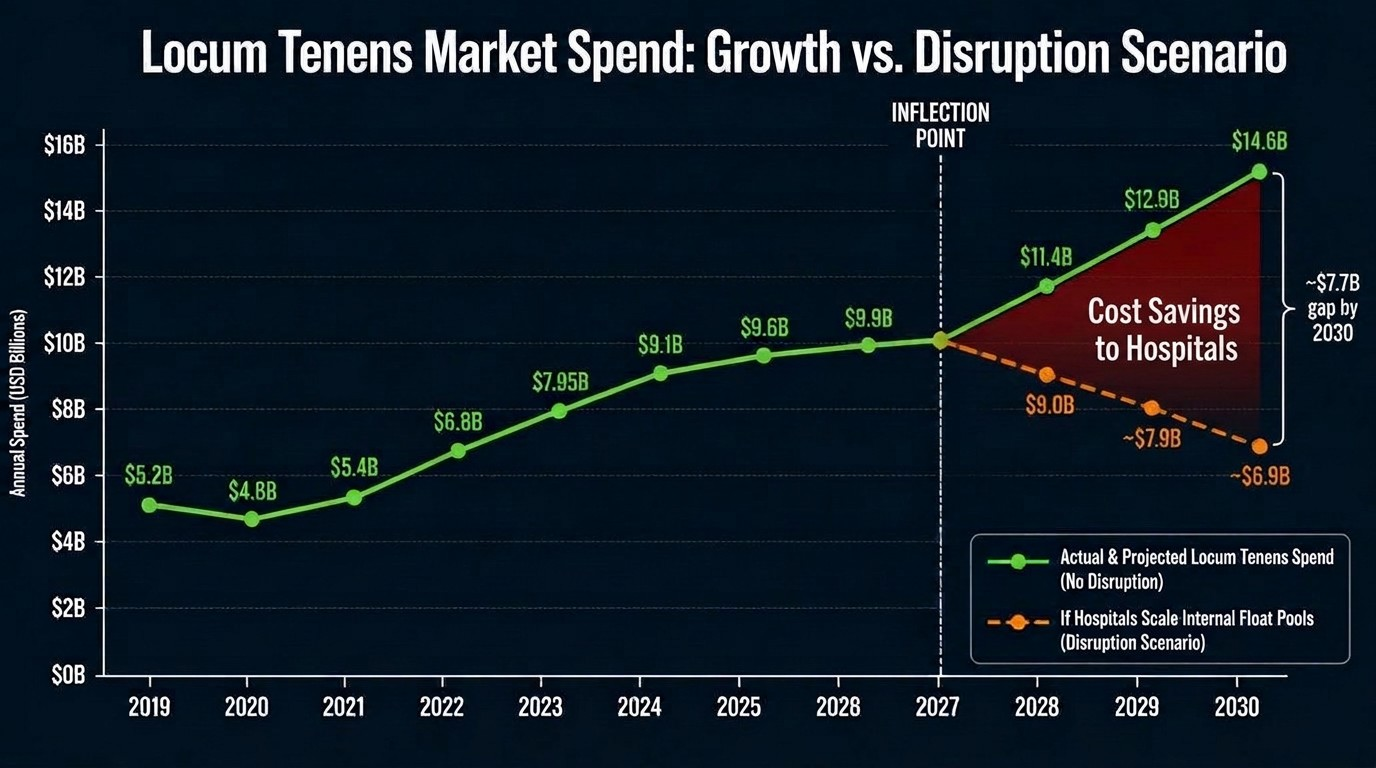
Locum tenens spend has nearly doubled since 2019 and is on track to hit $14.6B by 2030, but hospitals could redirect roughly $7.7B of that by scaling internal float pools instead of renting from outside agencies. Beyond the savings, owned float pools give hospitals more control over staffing, better continuity of care, and physicians who are culturally aligned rather than transient contractors. The window to build this advantage is now, before the rest of the market catches on.
The locum tenens industry has quietly become one of the fastest-growing corners of healthcare staffing. In 2019, U.S. spend on locum tenens sat at roughly $5.2 billion. By 2025, it had nearly doubled to $9.6 billion, and every major staffing analyst covering the space projects it will keep climbing, with some forecasts putting the market north of $14 billion by 2030.
That growth isn't a fluke. It's the direct result of a physician workforce under siege: deepening specialty shortages, an aging clinician base heading toward retirement, rising chronic disease burden, and burnout pushing more physicians toward flexible, non-permanent work. Locum tenens has gone from an occasional stopgap to a load-bearing pillar of how hospitals keep the lights on.
But there's a problem hiding inside that growth curve. Every dollar flowing into the locum tenens market is a dollar flowing out of the hospital system and into third-party staffing agencies, agencies that markup bill rates, control the talent relationship, and have no long-term stake in a hospital's culture, quality metrics, or patient outcomes. Hospitals have essentially been renting their way through a workforce crisis. And renting, as any CFO will tell you, is rarely the cheapest way to solve a permanent problem.
The Alternative Nobody Scaled Properly, Until Now
Internal float pools aren't a new idea. Most health systems have some version of one: a small internal roster of clinicians who can flex across departments or facilities to cover gaps. But historically, float pools have been treated as a minor operational patch rather than a strategic alternative to external staffing spend. They're underfunded, understaffed, and rarely built with the technology, incentive structures, or scale needed to meaningfully displace locum tenens spend.
That's starting to change. As the locum tenens market approaches an inflection point, call it 2026 to 2027, a small number of forward-thinking health systems are asking a different question: what if we scaled the float pool instead of scaling our locum agency spend?
The financial logic is compelling. If a hospital system invests now in building a professionally managed, technology-enabled internal float pool, one that recruits, credentials, schedules, and retains its own bench of physicians and APPs the same way an external staffing firm would, the growth curve doesn't just slow. It can reverse.
Modeling the Disruption
Based on current locum tenens growth trajectories and a scenario in which health systems meaningfully scale internal float pools starting around the 2026-2027 inflection point, the spend divergence looks like this:
Status quo path: Locum tenens spend continues its current trajectory, reaching an estimated $11.4B by 2028, $12.9B by 2029, and $14.6B by 2030.
Float pool disruption path: If hospitals aggressively scale internal float pools starting at the inflection point, external locum spend could instead decline to roughly $9.0B by 2028, $7.9B by 2029, and $6.9B by 2030.
That gap, status quo versus disruption, works out to approximately $7.7 billion in avoidable spend by 2030, and a meaningful chunk of that, roughly $5 to $6 billion, would already be realized within the first three years of serious float pool investment.
It's Not Just About the Money
The dollar savings are the headline, but they're arguably not even the most important reason to make this shift. Three other benefits matter just as much, and in some cases, more, to the physicians and patients living inside these systems every day.
1. Control Over Staffing
When a hospital depends on an external locum agency, it is, by definition, dependent on someone else's bench, someone else's pricing power, and someone else's priorities. Bill rates spike during high-demand periods precisely when a hospital has the least leverage to push back. Coverage gaps get filled by whoever the agency has available, not necessarily who's the best fit. An internal float pool flips that dynamic. The hospital owns the pipeline, sets the terms, and can flex capacity to its own actual demand patterns rather than negotiating from a position of urgency every time a shift opens up.
2. Better Continuity of Care
Locum tenens clinicians, by design, are transient. They rotate through unfamiliar EHR systems, unfamiliar care teams, and unfamiliar patient populations, often for assignments measured in weeks. That discontinuity has a real cost that doesn't show up on a staffing invoice: onboarding friction, inconsistent documentation habits, and patients who see a different face every time they come in for follow-up care. An internal float pool clinician, by contrast, is still part of the same health system. They know the EHR. They know the care protocols. They may even know the patient. Continuity isn't just a patient-satisfaction metric, it's directly tied to readmission rates, diagnostic accuracy, and the kind of longitudinal trust that drives better outcomes.
3. Cultural and Clinical Alignment
This is the piece that's easiest to underestimate and hardest to buy externally. A locum physician, however skilled, is a guest in someone else's institution. They haven't been trained in that system's specific clinical protocols, quality initiatives, or cultural norms around communication, escalation, or teamwork. An internal float pool clinician has already been onboarded into the health system's culture. They understand its values, its shorthand, its way of doing things. That alignment translates into smoother handoffs, fewer care-team friction points, and physicians who feel like part of the mission rather than a temporary contractor passing through.
What It Actually Takes to Build One
Scaling an internal float pool from an afterthought into a genuine strategic asset requires treating it like the staffing business it effectively is. That means:
Dedicated recruitment and credentialing infrastructure, the same rigor an external agency applies, but built in-house and optimized for speed.
Technology for scheduling and deployment, real-time visibility into where gaps exist across the system, so float clinicians can be deployed proactively rather than reactively.
Competitive, transparent compensation: float pool clinicians need to be paid in a way that's genuinely competitive with locum rates, or the incentive to join simply won't be there.
A retention strategy, not just a staffing strategy: the whole point is longevity and cultural fit, so career pathing, flexibility, and a real sense of belonging matter as much as the paycheck.
Executive sponsorship and multi-year investment: this isn't a project that pays off in one budget cycle. The savings curve above assumes sustained investment starting at the inflection point, not a single pilot program.
The locum tenens market's growth trajectory isn't slowing down on its own, physician shortages and demographic pressure guarantee that demand for flexible staffing keeps rising. The only real question is whether hospitals keep paying an ever-growing premium to rent that flexibility from external agencies, or whether they build the capability to own it internally.
The math suggests the opportunity is real: potentially billions of dollars in avoidable spend over the next several years, alongside meaningfully better continuity of care and a physician workforce that's culturally embedded rather than transient. For health systems willing to make the upfront investment, scaling an internal float pool isn't just a cost play, it's a strategic hedge against a labor market that's only going to get tighter.
The hospitals that start building now, before the rest of the market catches on, are the ones most likely to capture that $7.7 billion opportunity, rather than watching it get captured by the staffing agencies they're currently paying.
Rate This Article
Click a star to rate
If any of this resonates — or you want to pressure-test these frameworks against your own data — I'm happy to connect. No pitch, just a conversation.
Schedule a Meeting →